Spain: Six measles cases have been confirmed in Mallorca in unvaccinated persons, representing the first cases reported in the Balearic Islands in 2026. The outbreak was identified on 7 August and linked to a paediatric tourist from another European country who attended the emergency department at Son Espases Hospital on 19 July. Secondary cases developed symptoms from late July onwards.
Sweden: On 17 Aug 2026, Swedish health authorities reported 19 measles cases linked to the Urkult festival in Näsåker (30 Jul–1 Aug), mostly among children under 18 years. Cases have been reported across several Swedish regions. As the festival attracted visitors from Sweden and other EU countries, further spread is possible.
Measles outbreaks are increasing worldwide.
Measles spread quickly and can be dangerous - protection is simple: get vaccinated!
Swiss recommendations: All persons born after 1963 who have no documented protection against the infection (antibodies or 2 documented vaccinations) should be vaccinated twice with MMR vaccine at one-month interval. In the event of an epidemic in the region or contact with a measles case, vaccination is recommended from the age of 6 months.
A cluster of Andes hantavirus infections linked to the Dutch-flagged cruise ship MV Hondius in the South Atlantic has resulted in multiple cases among passengers and crew from several countries. The outbreak involves Andes virus (ANDV), the only hantavirus known to cause limited person-to-person transmission, typically through close and prolonged contact.
Updates on new reported cases between 8 and 15 May 2026:
New cases - three new cases after the after evacuation from the cruise ship:
Total cases:
Other news:
Additional cases among cruise ship passengers remain possible due to the long incubation period of hantavirus infection, which can last up to 6–8 weeks. However, current response measures — including quarantine of disembarked passengers, rapid isolation of suspected cases, and contact monitoring — are expected to reduce the risk of further transmission.
Hantaviruses are rodent-borne zoonotic viruses transmitted to humans primarily through contact with contaminated rodent urine, droppings, or saliva. Human infections are rare but can cause severe and sometimes fatal disease.
Two main clinical syndromes are associated with hantavirus infection:
Transmission: Most hantaviruses are associated with specific rodent reservoir species that carry the virus without apparent illness. Human-to-human transmission is not typically and has only been documented with Andes virus in South America, primarily among close and prolonged contacts. Exposure risk increases during activities that disturb rodent-contaminated environments, such as cleaning enclosed spaces, farming, forestry work, or sleeping in rodent-infested dwellings.
Symptoms usually begin 1–8 weeks after exposure and include fever, headache, myalgia, abdominal pain, nausea, and vomiting.
Diagnosis can be difficult in the early stages because symptoms overlap with influenza, COVID-19, leptospirosis, dengue, viral pneumonia, and sepsis Confirmation relies on serology, especially IgM or rising IgG titres, and RT-PCR during acute illness.
Treatment: There is no licensed specific antiviral treatment or vaccine. Management is supportive, with close monitoring and treatment of respiratory, cardiac, and renal complications. Early recognition and access to intensive care when needed are essential to improve survival.
The risk to the general population is considered very low, while the risk for cruise ship passengers is assessed as moderate. Of note: Even if transmission from evacuated passengers occurs, widespread community spread is unlikely, as Andes virus (ANDV) does not transmit easily and infection prevention measures are in place.
Travel in areas where hanta virus is: Very low risk for travellers.
As of March 2026, mpox transmission continues globally across all clades, with clade Ib now confirmed for the first time in Argentina, Ecuador, Austria, the Central African Republic, Russia and Singapore and community transmission documented in five European countries (Austria, Belgium, Portugal, Spain, and the UK).
Sustained community transmission in Madagascar (clade Ib), Pakistan.
DRC Ministry of Health officially declares the end of the mpox epidemic as a national public health emergency on April 2, 2026.
A recombinant clade Ib/IIb strain has been detected in two travelers, with evidence suggesting wider circulation than currently documented (see WHO).
End of March, EMA’s committee for human medicines has issued a recommendation that Tecovirimat SIGA should not longer be used for the treatment of mpox (see EMA).
See also WHO global trends.
Risk very low for general populations but moderate for at risk groups.
Follow recommendations issued by local health authorities.
Since the beginning of 2025, and as of 20 August 2025, nine countries in Europe have reported human cases of West Nile virus infection: Albania, Bulgaria, France, Greece, Hungary, Italy, Romania, Serbia and Spain. Currently, 67 areas are known to be affected.
For updates, see ECDC LINK.
The following precautions are recommended:
If you have visited a West Nile fever transmission area, do not donate blood for at least 28 days after returning.
Germany: On 3 July 2025, German public health authorities reported detections of circulating vaccine-derived poliovirus type 2 (cVDPV2) in wastewater samples from multiple federal states:
Genetic sequencing shows the viruses closely match the cVDPV2 cluster previously detected in early 2025 in Spain, Poland, Germany, Finland, and the UK.
As of 3 July 2025, no clinical cases of poliomyelitis have been reported in the EU/EEA, and sustained human-to-human transmission within Germany has not been confirmed.
The large geographical spread in the EU/EEA, the fact that detections occurred over several months, and the identification of specific genetic sub-clusters suggest at least some degree of local transmission.
For all individuals, including refugees and migrants: Routine vaccination against polio according to national guidelines is important (Swiss FOPH recommendations | STIKO, Germany recommendations).
Travellers going to countries where wild poliovirus or polio vaccine virus is endemic should get vaccinated against polio, see recommendations on the country pages at www.healthytravel.ch.
On 06 Jun 2025, Spain reported a fatal case of human rabies in a 44-year-old male resident of the Valencian Community.
The patient had been bitten on the right leg by a dog during a trip to Ethiopia in July 2024. He cleaned the wound but did not seek medical attention or receive post-exposure prophylaxis (PEP). Approximately ten months later, he developed nonspecific symptoms, including fever, nausea, and mood changes. These progressed to hydrophobia, leading to a clinical suspicion of rabies. Despite intensive care, he died on 06 Jun 2025.
Spain, including its peninsular territory and islands, has been officially free of terrestrial rabies since 1978, with the exception of an isolated case in June 2013 involving a dog imported from Morocco. However, sporadic imported cases of rabies continue to be reported in the Autonomous Cities of Ceuta and Melilla, primarily involving dogs (four rabies dogs between April to June 2025) and occasionally horses.
This tragic case underscores the importance of awareness about rabies and the critical need for post- exposure prophylaxis following potential exposures, such as dog bites, in rabies-endemic travel destinations, see also rabies factsheet.
Prevention: Avoid contact with animals and do not feed them! Travelers are advised to get a pre-exposure vaccination, especially those at higher risk, such as individuals working with animals, riding two-wheelers, visiting remote areas, young children, cave explorers, or anyone who may come into contact with bats.
Behavior after exposure: After an animal bite/scratch: immediately wash the wound with water and soap for 15 minutes, then disinfect and in any case visit a high-quality medical center for post-exposure vaccination as soon as possible!
Several countries in the European Union have observed an increase in reported cases of hepatis A genotype 1B. In particular, Austria, Czechia and Hungary have observed more reported cases than expected between November 2024 to May 2025.
The increase of HAV infection is mainly affecting adults that are experiencing homeless, people with a drug addiction and people living in poor sanitary conditions. Two genetically closely related clusters of HAV 1b have been identified (cluster a and cluster b).
The chain of transmission is ongoing, and new cases are likely to occur.
Vaccination against hepatitis A is recommended for people visiting friends and relatives in remote rural areas and/or where hygiene conditions are poor as well as for risk persons, see SOP hepatitis A at www.healthytravel.ch PRO version.
Die Daten zu Masernfällen in der Europäischen Union und im Europäischen Wirtschaftsraum (EU/EWR) in den letzten zwölf Monaten (1. Februar 2024 bis 31. Januar 2025 32‘265 Masernfälle) zeigen einen deutlichen Anstieg der Meldungen im Vergleich zu 2023. Rumänien (27‘568), Italien (1‘097), Deutschland (637), Belgien (551) und Österreich (542) wiesen die höchsten Fallzahlen auf.
Aufgrund der vermehrten Viruszirkulation, werden die Fallzahlen sehr wahrscheinlich im Frühjahr 2025 zunehmen. Die anhaltende Übertragung deutet auf Lücken in der Durchimpfung gegen diese vermeidbare Krankheit hin – sowohl bei Kindern als auch bei Jugendlichen und Erwachsenen.
Lassen Sie Ihren Impfstatus überprüfen!
Alle nach 1963 geborenen Personen, die keinen nachgewiesenen Schutz gegen Masern haben (Antikörper oder 2 nachgewiesene Impfungen), sollten zweimal mit dem MMR-Impfstoff geimpft werden. Im Falle einer Epidemie in der Region oder bei Kontakt mit einem Masernfall wird die Impfung ab einem Alter von 6 Monaten empfohlen.
The data from the latest ECDC annual epidemiologic reports on sexual transmitted diseases (STIs) show the notification rate for confirmed gonorrhea cases in European Union/European Economic Area countries rose by 31% in 2023 compared with 2022 and has risen by 321% since 2014.
Syphilis cases also continue to rise. In 2023, 41’051 confirmed cases were reported in 29 EU/EEA countries, representing a 13% increase compared to 2022, and a doubling compared to 2014.
In the past 3 months, vaccine-derived poliovirus type 2 (VDPV2) was detected in sewage samples in Barcelona, Spain; Warsaw, Poland; and Bonn, Düsseldorf, Dresden, Hamburg, Cologne, Mainz and Munich, Germany. The detected virus is genetically linked to a strain that emerged in Nigeria. This strain is circulating in several countries outside the Region, most widely in North and West Africa.
In all 3 countries in the European Region, the virus was isolated from environmental (sewage) samples only – no associated paralytic cases of polio have been detected.
Germany, Poland and Spain maintain strong disease surveillance and high levels of routine immunization coverage, estimated at 85–93% nationally with 3 doses of inactivated polio vaccine (IPV), which provides excellent protection from paralysis caused by poliovirus.
However, pockets of undervaccination exist in every country.
The detection of VDPV2 in wastewater is not surprising. People can shed the virus if they come from or have travelled to countries where oral poliovirus vaccine is still used. The risk for vaccinated people in Germany is very low due to the high vaccination coverage against polio.
For all individuals, including refugees and migrants: routine vaccination against polio according to national guidelines is important (Swiss FOPH recommendations |STIKO, Germany recommendations). Travellers going to countries where wild poliovirus or polio vaccine virus is endemic should get vaccinated against polio, see recommendations on the country pages at www.healthytravel.ch.
In 2024 and as of 2 October 2024, 18 countries in Europe have reported 1’202 locally acquired human cases of West Nile Virus (WNV) infection with known place of infection. The earliest and latest date of onset were respectively on 1 March 2024 and 26 September 2024.
Locally acquired cases were reported by Italy (422), Greece (202), Spain (114), Albania (102), Hungary (101), Romania (71), Serbia (53), Austria (34), Türkiye (30), France (27), Croatia (20), Germany (8), Slovenia (5), Kosovo (4), Slovakia (4), Bulgaria (2), North Macedonia (2) and Czechia (1).
In Europe, 88 deaths were reported by Greece (31), Italy (16), Albania (13), Romania (10), Spain (10), Bulgaria (2), Serbia (2), Türkiye (2), France (1) and North Macedonia (1).
Case numbers reported this year are above the mean monthly case count for the past 10 years. During the same period in 2023, 681 cases had been reported. However, numbers are lower than in 2018, when 1 728 cases had been reported by this time of year.
Distribution of locally acquired human West Nile virus infections in 2024 till 2 October 2024:
Of note, further regions of infection were reported in 2023.
The following precautions are recommended:
In the beginning of May 2022, one case of monkeypox was detected in England, which had occurred after travel to Nigeria. In the course of this, 6 further cases of monkeypox were diagnosed in England in people with no previous travel and no contact with known travel-associated cases. These are two cases in one family and four cases in men who have sex with men (MSM). The latter apparently got infected in London. Apart from the family and two of the MSM cases, there are no known links between the cases. Further 2 cases have been reported in the meantime. Investigations into the sources of infection and other suspected cases are in progress.
Additional cases are reported by GeoSentinel and various media reports from the following countries:
Description: Monkeypox is a zoonosis caused by an orthopoxvirus, a DNA virus genetically related to the variola and vaccinia viruses. Monkeypox is endemic in West and Central Africa. Increased cases have been recorded in Nigeria since September 2017, and imports by returning travellers to England and the USA have also been recorded more frequently in recent years. There are two types of monkeypox virus: the West African type and the Central African type (Congo Basin).
Transmission: Monkeypox is transmitted from infected animals by a bite or by direct contact with blood, body fluids or lesions of the infected animal. It can be transmitted via abrasions in the mouth to people who eat infected animals. It can also be transmitted from person to person via the respiratory tract, through direct contact with body fluids of an infected person or with virus-contaminated objects. The incubation period is 5-21 days, usually about 7 to 17 days.
Symptoms: Symptoms of monkeypox include fever, headache, muscle aches, swollen lymph nodes and chills. 1- 3 days after the onset of symptoms, a rash develops that may look like chickenpox or syphilis and spreads from the face to other parts of the body, including the genitals. The disease is usually mild. In immunocompromised individuals, the disease can be severe. The mortality rate is about 1% for the West African type and up to 10% for the Central African type.
For further details, see WHO factsheet, ECDC and CDC.
Further cases must be expected. Persons showing symptoms as described above should contact a doctor, ideally in advance by telephone. Persons who have several sexual partners or practice casual sex should be particularly vigilant!
Prevention: Good personal hygiene, avoid contact with infected persons and animals at all costs. During stays in West and Central Africa: No consumption of bushmeat. The individual risk of contact with a patient with monkeypox depends on the type and duration of contact. In the case of very close contact with a case (e.g. family members, aeroplane neighbours, medical personnel), the risk of infection has so far been classified as moderate; in the case of sexual / intimate contact, it is probably high.
Source image: NCDC
WHO 18.5.2022, RKI 19.5.2022, UK GOV, 16.5.2022, Outbreak News Today, 18.5.2022, CDC, Labor Spiez
All travellers should have completed a basic immunisation according to the Swiss vaccination schedule, LINK.
In cases of incomplete or unknown immunization status, catch-up vaccinations are strongly recommended, and individuals should be followed up until the vaccination series is completed (note: environmental samples have tested positive for cVDPV2).
EKRM_Factsheet_Layperson_EN_Polio.pdf
Regular hand washing after using the bathroom and before eating or preparing food. Avoidance of undercooked or raw food that is potentially contaminated with fecal material.
The most important prevention is vaccination. A very effective and well-tolerated vaccine against polio is available (inactivated (killed) polio vaccine (IPV)), which is part of the basic vaccination schedule during childhood. Combination vaccines (e.g. with diphtheria and tetanus) are also available. After basic vaccination, a booster dose is recommended every 10 years for travel to certain countries (see country page recommendations). WHO recommends a yearly vaccination for residents or long-stay visitors (minimum 4 weeks) in a country with ongoing polio infections or circulating vaccine-derived polio viruses. This recommendation not only targets individual protection, but aims to prevent the international spread of the virus.
All travellers should have completed a basic immunisation and boosters according to the Swiss vaccination schedule, LINK.
General information on measles, mumps and rubella (MMR)
Please consult the following FOPH links:
Travellers should be immune to chickenpox. Persons between 13 months and 39 years of age who have not had chickenpox and who have not received 2 doses of chickenpox vaccine should receive a booster vaccination (2 doses with minimum interval of 4 weeks), see Swiss vaccination schedule, LINK.
Please consult the following link of the FOPH:
General information about chickenpox (varicella) and shingles (herpes zoster)
No treatment against rabies disease exists!
Post-exposure measures: clean the wound immediately with plenty of water and soap for 10-15 minutes, then disinfect the wound (e.g. Betadine®, Merfen®), and immediately (i.e. during the trip!) get emergency post-exposure vaccination against rabies: for those having received full pre-exposure rabies vaccination before travel, two additional vaccine shots (any available brand) at an interval of 3 days suffice and should be administered as soon as possible on site (i.e. also while travelling). If full pre-exposure vaccination has not been given, in addition to vaccination, passive immunization is required with immunoglobulins within the shortest delay on site.
Of note, immunoglobins (and sometimes vaccines) are often unavailable in low-resource settings, causing stress and uncertainty. Tetanus booster vaccination may be also warranted.
Petting any mammals while travelling is not a good idea, even if they are cute! Do not feed them! Refrain from touching wild or unfamiliar or dead animals.
Vaccination against rabies (preexposure vaccination) is recommended for most travellers, and is particulary recommended for:
The shortened vaccination schedule can be proposed to most travellers: 2 doses given at least 7 days apart before departure. A single lifetime booster dose (3rd dose) is recommended after one year or later when further travelling to rabies endemic countries is undertaken. If you have an immune deficiency, please consult your doctor, as different vaccination intervals apply to you.
Depending on the geographical region and the species, ticks may carry and transmit different pathogens. Diseases include the human ehrlichiosis, Lyme disease, tularemia, babesiosis, tick-borne relapsing fever, Rocky Mountain spotted fever, other rickettsioses, some arboviral diseases, and several flaviviruses causing encephalitis such as tick-borne encephalitis (TBE). Some ticks may also cause tick paralysis.
In Europe, commonly transmitted disease by ticks include Lyme disease (borreliosis), tick-borne encephalitis and tularemia.
In the US (and less so in South America) important tick-borne diseases represent babesiosis, anaplasmosis and ehrlichiosis, Powassan disease and severe fever with thrombocytopenia syndrome (STFS).
Other important pathogens transmitted by ticks are bacterial organisms causing rickettsial diseases, which are found throughout the world. Among returned travelers, rickettsial diseases have been estimated to be the fourth most common cause of fever, with symptoms such as rash, abdominal pain, and a dry, black/dark scab at the site of the infecting bite.
Tick-borne diseases may occur worldwide, but distribution is based on geographical location (see map).
Areas with increased risk of TBE include central and eastern Europe and the Baltic and Nordic countries. TBE is also prevalent in Russia all the way from the western border with Europe to its eastern border.
Lyme borreliosis is the most prevalent tick-transmitted infection in temperate areas of Europe, North America and Asia, and its geographic distribution is ever-increasing. Central Europe is the region with the highest tick infection rates (young ticks/nymphs >10%; adult ticks >20%) in Europe, specifically in Austria, Czech Republic, southern Germany, Switzerland, Slovakia and Slovenia.
Babesiosis is found in certain regions of North America and forested areas in Europe and East Asia. Anaplasmosis is common in North America, Europe, and China.
Ehrlichiosis is common in the US, certain areas of Europe, South America, and Africa.
Powassan disease is found in the northeastern US and far eastern Russia, whereas Severe Fever with Thrombocytopenia Syndrome (SFTS) occurs in the US and Asia-Pacific region.
Rickettsial infections are present worldwide. African Tickbite Fever (ATBF) is the most commonly reported rickettsial infection acquired during travel and occurs in southern Africa (especially Botswana, South Africa, and Zimbabwe).Mediterranean Spotted Fever (MSF), reported among returning US and UK travelers, occurs over much of Africa, Europe, India, and the Middle East; whereas Rocky Mountain Spotted Fever (RMSF) is commonly found throughout Canada, parts of Central and South America, and the US.
Crimean-Congo hemorrhagic Fever (CCHF) is a rare but serious viral disease transmitted by tick bites or contact with infected animal blood. It is the most widespread viral hemorrhagic fever, found in Eastern and Southern Europe, the Mediterranean, northwestern China, central Asia, Africa, the Middle East, and the Indian subcontinent. Healthcare workers and those handling livestock face higher risk.
The key to prevent tick-borne diseases is to protect yourself from tick bites (see also fact-sheet "Mosquito and tick bite prevention"):
The best prevention against tick-borne encephalitis (TBE) is to get vaccinated; this is recommended if living or travelling in an endemic area. The vaccine protects against all virus subtypes.
General informations about seasonal flu (influenza)
Please consult the following FOPH links:
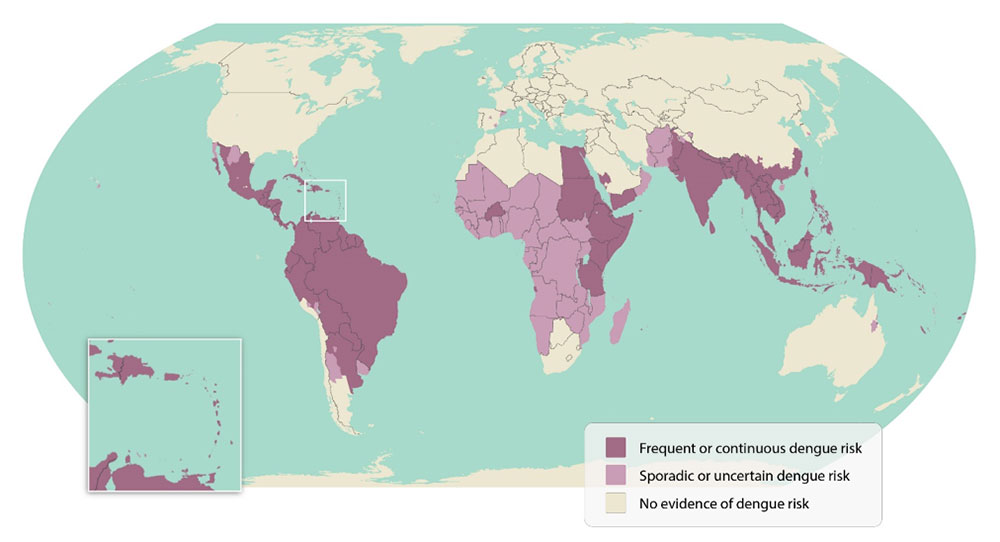
During 2018 the first locally acquired dengue cases were reported, with transmission occurring in the provinces of Cádiz, Catalonia and Murcia. Risk is low.
Dengue_Factsheet_Public_ECTM_EN.pdf
Insect_and_Tick_Bite_Protection_Factsheet_Public_ECTM_EN.pdf
In 3 out of 4 cases, an infection with the virus remains asymptomatic. After a short incubation period (5-8 days), 1 out of 4 infected people present an abrupt onset of fever, headache, joint, limb and muscle pain, as well as nausea and vomiting. Painful eye movement is also typical. A rash may appear on the 3rd or 4th day of illness. After 4 to 7 days, the fever subsides but fatigue may persist for several days or weeks.
In rare cases, severe dengue can occur. Particularly susceptible are local children and seniors, as well as people who have experienced a prior dengue infection. Tourists very rarely present with severe dengue. In the first days, severe disease resembles the course of classic dengue fever, then on the 4th/5th day, and usually after the fever has subsided, the condition worsens. Blood pressure drops, and patients complain of shortness of breath, abdominal discomfort, nosebleeds, and mild skin or mucosal hemorrhages. In the most severe cases, life-threatening shock may occur.
There is no specific treatment for dengue virus infection. Treatment is limited to mitigation and monitoring of symptoms: fever reduction, relief of eye, back, muscle and joint pain, and monitoring of blood clotting and blood volume. Patients with severe symptoms must be hospitalized.
For the reduction of fever or pain, remedies with the active ingredient paracetamol or acetaminophen are recommended (e.g. Acetalgin® Dafalgan®). Drugs containing the active ingredient acetylsalicylic acid (e.g. Aspirin®, Alcacyl®, Aspégic®) must be avoided.
Effective mosquito protection during the day and especially during twilight hours (i.e. sunset) is the best preventive measure:
For further information, please refer to the factsheet on "Mosquito and tick bite protection".
Note on the dengue vaccine Qdenga®:
Consistent mosquito protection during the day (see above) is still considered the most important preventive measure against dengue!
There is a risk of arthropod-borne diseases other than malaria, dengue, chikungunya or zika in sub-/tropical regions, and some areas of Southern Europe. These include the following diseases [and their vectors]:
Enjoying your sexuality freely and responsibly is part of a healthy life. Knowing how to take care of yourself and others is especially important when you are in new situations – like during travel.
Travelers who engage in casual sex tend to be at higher risk of contracting sexually transmitted infections (STIs), including HIV. Being abroad, while also meeting new people, can involve behaving differently and taking more risks than you would at home. It is important to know that certain practices – such as unprotected sex and/or having multiple new sexual partners – can significantly increase the risk for STIs. Some STIs can cause serious complications in some circumstances and can also be transmitted to additional partners if not diagnosed and treated in time. If you are not sure whether you are at risk, Love Life's 'Risk Check' can help.
Important: STIs can also occur without any or only mild symptoms. Even if you are not aware of it, you can infect others. Even if you have no symptoms, you should consult your doctor if you have had unprotected sex with a new partner or multiple partners. This is because early detection and treatment are important to prevent transmission and complications from untreated STIs.
STIs can be diagnosed during a physical exam or by examining urine, a sore, a blister, or a swab from the vagina, penis, throat or anus. Blood tests can help with certain diagnosis (hepatitis A, B and C, HIV and syphilis).
The timing of testing is important, as some infections may not be detectable immediately after exposure (diagnostic window). To rule out an infection, HIV and syphilis should usually be tested at least 6 weeks after the sexual contact. In the case of chlamydia and gonorrhea, testing should be done at least 2 weeks after the contact. This applies only if there are no symptoms.
Take also into consideration that access to reliable testing and treatment may be limited in some destinations.
Before you travel:
During travel:
Mpox has been commonly found in West and Central Africa for many years where the suspected reservoir - small mammals - is endemic. There are two types of Monkeypox virus called ‘clades’ that cause the disease mpox - clade I in Central Africa and clade II in West Africa. Since the end of smallpox vaccination campaigns in the early 1980’s, cases of mpox have increased, slowly at first and significantly in the last 5-10 years, especially in the Democratic Republic of Congo (DRC).
In 2022, a new emerging subclade of clade II was responsible for a global epidemic that spread mainly through sexual contact among men who have sex with men. It resulted in the first public health emergency of international concern (PHEIC) declared by the WHO until 2023. Although the clade II epidemic is now under control, this virus variant continues to circulate worldwide.
In 2024, the continued spread of mpox clade I in endemic regions of Central Africa, particularly in the DRC, and the emergence of a new subclade Ib in Eastern DRC and neighboring countries have raised global concern and prompted the WHO to declare a PHEIC for the second time in two years. The current geographical spread of the mpox clade Ib variant occurs via commercial routes through sexual contact (e.g. sex workers), followed by local transmission in households and other settings (which is becoming increasingly important).
Animal to human transmission
Mpox can spread from animal to human when they come into direct contact with an infected animal (rodents or primates).
Human to human transmission
Mpox can be spread from person to person through close physical contact (sexual and non-sexual contact) with someone who has symptoms of mpox. Skin and mucous membrane lesions, body fluids, and scabs are particularly infectious. A person can also become infected by touching or handling clothing, bedding, towels, or objects such as eating utensils/dishes that have been contaminated by contact with a person with symptoms. Household members, family caretakers, and sexual partners of a confirmed case of mpox are at higher risk for infection as are health care workers who treat a case without adequate personal protection.
The incubation period (time between infection and onset of symptoms) ranges from a few days up to 3 weeks. Mpox causes a rash / skin eruption that can be painful associated with swollen lymph nodes and fever. Fever may start already before the rash phase. Other symptoms include muscle aches, back pain, and fatigue. The rash may be localized or generalized, with few or hundreds of skin lesions. It mainly affects the face, the trunk and the palms of hand and soles of the feet. It can also be present in genital areas and on mucous membranes such as in the mouth and throat. Symptoms usually last 2 to 4 weeks and the person remains contagious until all lesions have healed (once the cabs have fallen off).
Complications include secondary bacterial infections, infections of the lung and brain and involvement of other organs, still birth and others. Children, pregnant women, and people with weak immune systems are at higher risk to develop a severe form of mpox.
The majority of person with mpox recovers spontaneously and do not need specific antiviral treatment. Care management consists of relieving pain and other symptoms and preventing complications (e.g., superinfection). Several antiviral treatments are studied in various countries and may be used in trials or in clinical situations according to the recommendations of national medical societies.
In case of symptoms:
General precautions:
Vaccination:
There are several vaccines against mpox (e.g. Jynneos®, manufacture Bavarian Nordic). The Bavarian Nordic vaccine was originally developed to fight against smallpox, but offers a cross-protection against mpox. In Switzerland, the Jynneos® vaccine has been licensed by Swissmedic since 2024. Groups at risk (e.g., men who have sex with men or transgender people with multiple sex partners) are eligible for vaccination since 2022 and this recommendation remains unchanged (see FOPH recommendations). In light of the epidemiological situation in Africa in 2024, the Swiss Expert Committee for Travel Medicine recommends vaccination against mpox for professionals who are / will be in contact with suspect mpox patients or animals in endemic/epidemic regions or who work in a laboratory with the virus (for updates, see news).
The risk to the general population and travelers (tourists) is considered extremely low if the above-mentioned general precautions are followed and vaccination is not recommended.
0